
What’s Known
It is not clear why some severe hemophilia A patients develop inhibitors; however, previous research supports a role for cytokines. Interleukin-6 is an essential cytokine in antibody production, and our previous study showed the abnormal plasmablast frequency in severe hemophilia A patients with inhibitors.
What’s New
This is the first study in Iran, showing that severe hemophilia A patients with inhibitors had higher interleukin-6 levels than inhibitor-negative patients. Interleukin-6 levels correlated positively with inhibitor titers. Interleukin-6 may serve as a valuable biomarker for assessing the risk of inhibitor formation.
Introduction
Hemophilia A (HA) is an X-linked recessive disorder and the most common inherited bleeding disease, caused by mutations in the gene encoding coagulation factor VIII (FVIII) located on the long arm of the X chromosome.1 This defect leads to a quantitative or qualitative deficiency of FVIII. The global incidence of HA is approximately 1 in 5,000 live male births. Based on the residual FVIII activity, the disease is classified into mild, moderate, and severe forms.2
The primary therapeutic approach for patients with severe HA is the replacement of FVIII activity using recombinant or plasma-derived FVIII concentrates.3 However, the development of neutralizing antibodies, known as inhibitors, remains one of the most significant complications of FVIII replacement therapy, affecting approximately 20–25% of patients with severe HA.3 These inhibitors bind to and inactivate the infused FVIII, thereby diminishing its therapeutic efficacy and rendering treatment less effective.3
Several factors have been implicated in the development of inhibitors, including the type of genetic mutation, family history, race, human leukocyte antigen (HLA) class I/II, disease severity, as well as treatment-related factors such as the type of FVIII concentrate (plasma-derived or recombinant), treatment frequency, and age at initiation of prophylaxis.3-5
Recent studies have also suggested that single-nucleotide polymorphisms in immune response genes, including interleukin-10 (IL-10) and tumor necrosis factor-α (TNF-α), as well as alterations in plasma levels of specific cytokines such as IL-10 and TNF-α, may contribute to inhibitor formation in HA patients.4, 6-8
IL-6 is a multifunctional pro-inflammatory cytokine that plays a key role in numerous physiological and pathological processes, including acute-phase responses and autoimmune/inflammatory diseases.9-12 IL-6 promotes T-cell resistance to apoptosis, enhances T-helper cell activation, and regulates the balance between Th17 cells and regulatory T lymphocytes (Tregs).9, 10 Consequently, targeting IL-6 signaling has been explored as a potential therapeutic strategy for various inflammatory disorders. Importantly, IL-6 is a critical factor for B-cell maturation and promotes antibody production.9, 10 It is also essential for the induction and maintenance of plasma cells that secrete immunoglobulin subclasses.13, 14 Furthermore, IL-6 supports germinal center formation and somatic hypermutation, processes that are crucial for the generation of high-affinity antibodies.13, 14
Data on IL-6 levels in HA patients remain limited; however, elevated IL-6, together with increased soluble IL-6 receptor α (sIL-6Rα), has been associated with bleeding episodes and joint inflammation, contributing to the development of hemophilic arthropathy.15, 16
Nevertheless, the relationship between plasma IL-6 levels and inhibitor development in HA patients is not fully understood. In a previous study by our group, we observed differences in plasma blast frequencies, particularly in the inhibitor-positive group, but the underlying mechanisms for this variation remain unclear.17
Given the critical role of IL-6 in plasma cell differentiation and antibody production, the present study aims to evaluate plasma IL-6 levels in patients with severe HA and investigate their association with inhibitor development and plasma blast frequencies in these patients.
Patients and Methods
Study Population and Selection Criteria
This is the first case-control study in Iran, conducted on thirty-two male patients with severe HA who received education and follow-up care at the Comprehensive Hemophilia Center affiliated with Shiraz University of Medical Sciences between January and December 2022.
Due to the limited number of severe HA patients with inhibitors, all available cases of severe congenital HA with inhibitors (inhibitor+) were enrolled. Additionally, 24 inhibitor-negative severe HA patients (inhibitor-) and 24 healthy controls were included in the study. The sample size was defined based on the study by Irigoyen and colleagues.18 All patients had received FVIII either on-demand or as prophylaxis within 3 to 10 days before sampling.
Inclusion criteria were patients with severe HA (factor VIII activity <1%). Exclusion criteria included a history of collagen vascular or chronic infectious diseases; positive serologic results for hepatitis B or C and/or bacterial infections within the preceding two months; history of immunosuppressive drug use (such as glucocorticoids or cyclosporine); or any confirmed autoimmune, inflammatory, or allergic disorders. None of the patients had previously undergone immune tolerance induction. All participants exhibited joint involvement.
Healthy controls were defined as individuals with no history of chronic inflammatory diseases (e.g., rheumatoid arthritis, inflammatory bowel disease, psoriasis), no acute or chronic infections (including HIV, hepatitis B/C, tuberculosis), no malignancy, and no use of immunosuppressive or anti-inflammatory medications within the 4 weeks before blood collection.
The study protocol was approved by the Institutional Ethics Committee of Shiraz University of Medical Sciences (IR.SUMS.MED.REC.1402.247), and written informed consent was obtained from all participants and/or their legal guardians.
Factor VIII Activity and Inhibitor Assay
Factor VIII activity levels were measured using a clotting-based assay on an automated coagulation analyzer (ACL TOP CTS 300; Instrumentation Laboratory, USA). Inhibitor titration was performed according to the Bethesda assay protocol, both with and without heat treatment at 56 °C for 30 min, to detect antibodies directed against FVIII.
Plasma Sample Preparation
Five mL of fresh peripheral blood was collected in tubes containing ethylenediaminetetraacetic acid (EDTA). Samples were centrifuged at 1500 rpm for 10 min to separate the plasma, which formed the upper layer. The plasma fraction was then carefully collected and stored at -80 °C until further analysis.
Detection of Plasma IL-6 and Plasmablasts
Plasma IL-6 levels were determined using the enzyme-linked immunosorbent assay (ELISA) technique according to the manual instructions. The human 96-well IL-6 detection kit (Karmania Pars Gene, Iran) was used to measure plasma IL-6 levels in HA patients and control samples. Each sample was assayed in duplicate, and the mean of the two replicate wells was used as the measured value. The sensitivity of the IL-6 ELISA kit was 2 pg/mL, and the specificity of the kit was <3-4% (Intra-assay) and <8-10% (Inter-assay). The standard curve ranged from 0 to 300 pg/mL. Finally, the OD at 450 nm was read, and the concentration of the unknown sample was determined by plotting a standard curve. The frequency of CD19+IgD - CD27highCD38high plasmablast was previously defined in both severe HA patients and healthy controls using flow cytometry method.17
Statistical Analysis
Data were analyzed using SPSS software version 21 (IBM Corp., Armonk, NY, USA). Normality of the data was assessed using the Shapiro–Wilk test. The quantitative variables were compared between two groups using Student’s t-test for normally distributed data and the Mann–Whitney U test for non-normally distributed data. For comparisons among more than two groups, one-way ANOVA and the Kruskal–Wallis test were applied for parametric and non-parametric data, respectively. A post hoc power analysis was performed to define the statistical power of the primary comparison, using a General Linear Model (α=0.05, 95% confidence interval). The analysis yielded an observed power of 0.898, indicating that the study had sufficient power to detect the observed effect despite the relatively small sample size. To assess whether potential confounders influenced the primary outcome, a multivariate linear regression analysis was conducted with IL-6 as the dependent variable. The following independent variables were entered simultaneously using the Enter method: age, type of treatment, FVIII type, and inhibitor group. Correlations between quantitative variables were assessed using Spearman’s correlation test.
To evaluate the diagnostic performance of plasma IL-6 levels for distinguishing inhibitor-positive from inhibitor-negative patients, a receiver operating characteristic (ROC) curve analysis was performed. The area under the curve (AUC) was calculated with its 95% confidence interval (CI), with the optimal cut-off value >68.7 pg/mL for IL-6 levels. A P value less than 0.05 was considered statistically significant.
Results
In this study, a total of 32 male patients with severe HA, including 8 inhibitor-positive (inhibitor+) and 24 inhibitor-negative (inhibitor-) patients, along with 24 healthy male volunteers, were enrolled. The mean age of HA patients and healthy controls was 23.84±15.89 and 25.23±14.46 years, respectively. Clinical and laboratory characteristics of the HA patients are summarized in table 1.
| Variables | Inhibitor (+) (n=8) | Inhibitor (-) (n=24) | P value | |
|---|---|---|---|---|
| Age (years;mean±SD) | 12.14±5.9 | 27.25±2.97 | 0.05 | |
| Laboratory and clinical data | WBC count (×103/µL) | 6.23±0.95 | 6.07±0.32 | 0.846 |
| Platelets (×103/µL) | 323.33±63.72 | 250.62±16.9 | 0.122 | |
| Hb (g/dL) | 11.92±1.02 | 14.12±0.39 | 0.25 | |
| FVIII concentration (IU/ml) | 0.61±0.14 | 2.2±0.63 | 0.168 | |
| Anti-FVIII inhibitor titer (BU/ml) | 6.15±2.8 | <0.1 | ||
| WBC count (×103/µL) | 6.23±0.95 | 6.07±0.32 | 0.846 | |
| Received therapy | pFVIII | 6 | 6 | |
| rFVIII | 0 | 18 | ||
| Unknown | 2 | 0 | ||
| Type of treatment | On-demand | 3 | 16 | |
| Prophylaxis | 4 | 7 | ||
| Unknown | 1 | 1 | ||
| Joint affection | 8 (100%) | 24 (100%) | ||
| History of viral hepatitis | Positive | 0 | 2 | |
| Negative | 6 | 11 | ||
| Suspicious | 1 | 10 | ||
| Unknown | 1 | 1 | ||
| Data were analyzed using the Mann-Whitney test. A P value less than 0.05 was considered significant. SD: Standard deviation; WBC: White blood cells; Hb: Hemoglobin; p-FVIII: Plasma-derived FVIII; rFVIII: Recombinant FVIII | ||||
Quantification of Plasma IL-6 in HA Patients and Controls
Plasma IL-6 levels were measured and compared between HA patients and healthy controls. The IL-6 level was higher in HA patients than in controls, although the difference did not reach statistical significance (median 53.81 [range 28.96-114.44] vs. 51.2 [range 30.65-70.07] pg/mL; P=0.197; figure 1).
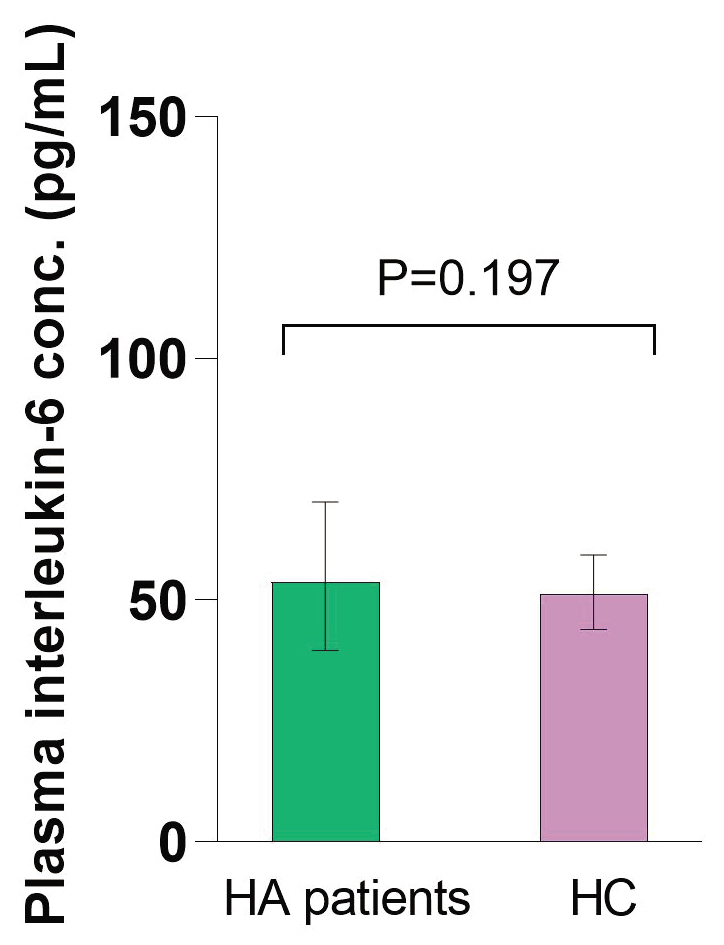
Figure 1.This figure shows the comparison of IL-6 levels between severe hemophilia A (HA) patients (n=32) and healthy controls (HC) (n=24). Data are presented as median values and were analyzed using Student’s t test. The error bars represent the Interquartile Range (IQR). A P value less than 0.05 was considered statistically significant. HA: Hemophilia A; HC: Healthy controls
Comparison of the Plasma IL-6 Levels between Inhibitor (+) Patients, Inhibitor (-) Patients and Healthy Controls
Plasma IL-6 levels were measured in inhibitor-positive (inhibitor +) and inhibitor-negative (inhibitor -) HA patients, as well as in healthy controls, and compared across the three groups. The mean IL-6 level was significantly higher in inhibitor-positive patients compared with inhibitor-negative patients and healthy controls (median 72.99 (range 38.14-114.44) vs. 47.62 (range 28.96-84.53) pg/mL, *P=0.001; and median 72.99 (range 38.14-114.44) vs. 51.2 (range 30.65-70.07) pg/mL, *P=0.001, respectively; figure 2). No significant difference was observed between inhibitor-negative patients and healthy controls regarding plasma IL-6 concentration (47.62±15.83 vs. 50.99±11.11 pg/mL; P=0.978; figure 2).
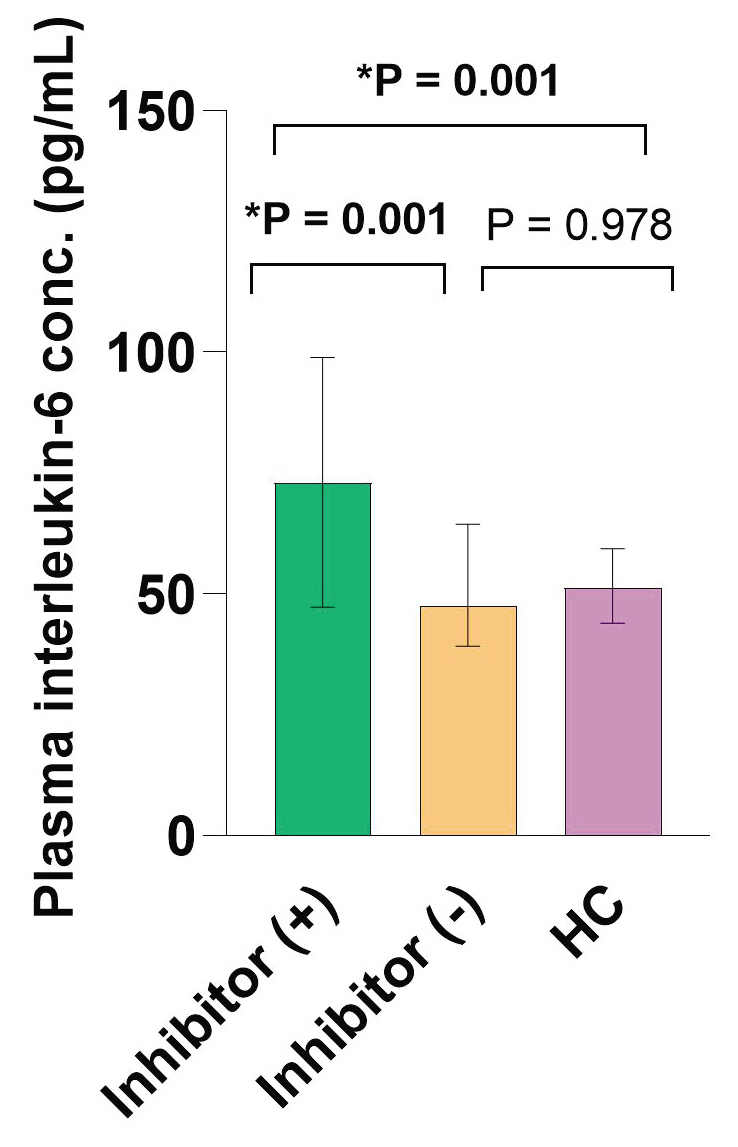
Figure 2.This figure represents a comparative analysis of plasma interleukin-6 (IL-6) levels across inhibitor-positive patients (n=8), inhibitor-negative patients (n=24), and healthy controls (HC) (n=24). Data are presented as median values and analyzed using ANOVA. The error bars represent the Interquartile Range (IQR). A P value less than 0.05 was considered statistically significant. HC: Healthy controls
Multivariate linear regression analysis controlling for inhibitor group, age, treatment type, and FVIII type, with IL-6 as the dependent variable, showed that age (P=0.301) and treatment type (P=0.183) did not significantly predict IL-6 levels, indicating that these potential confounders did not influence our primary findings. Importantly, the inhibitor group remained a significant predictor after adjustment (*P=0.013, B=-21.98). FVIII type was also significant (*P=0.01).
Correlation of the IL-6 Plasma Levels with Inhibitor Titers and Plasmablast Frequencies
The Spearman’s correlation test was performed to assess whether there is a relationship between the IL-6 plasma levels, inhibitor titers, and the frequency of plasmablasts. The results revealed that there was a significant correlation between the level of IL-6 and inhibitor titer (r=0.393, *P=0.026; figure 3). No significant correlation existed between IL-6 plasma levels and the percentages of plasmablasts in HA patients (r=0.173, P=0.208; figure 3).
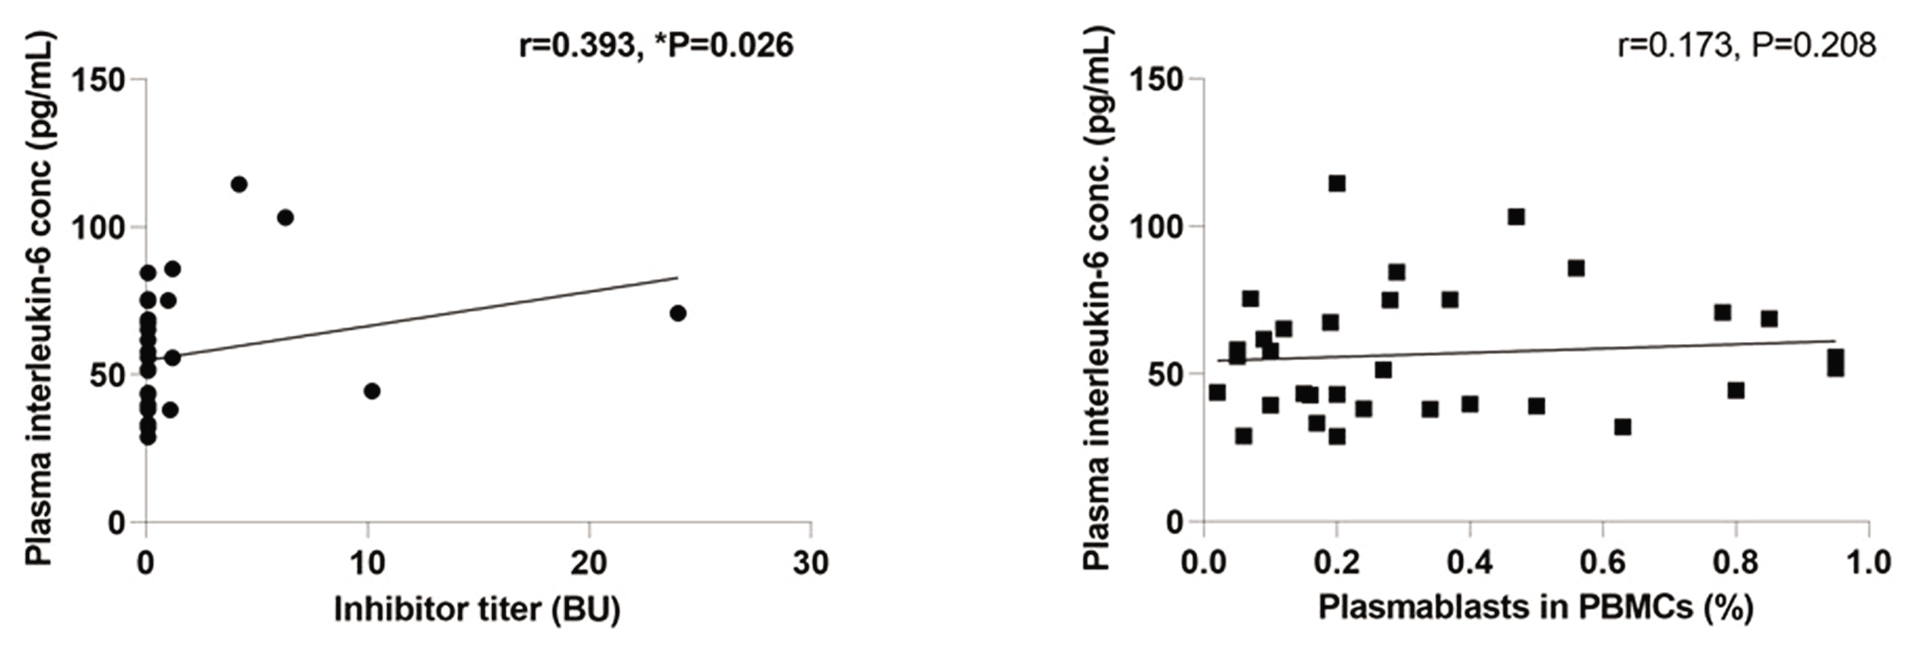
Figure 3.This figure shows the correlation of plasma IL-6 levels with inhibitor titers and plasmablast frequency. Data were analyzed using Spearman’s correlation test. A P value less than 0.05 was considered statistically significant. PBMCs: Peripheral blood mononuclear cells
IL-6 as a Biomarker for the Production of Inhibitors in Severe HA Patients
ROC curve analysis was performed to evaluate the diagnostic performance of IL-6 levels for distinguishing inhibitor-positive from inhibitor-negative patients (figure 4). ROC curve analysis demonstrated that IL-6 levels could significantly distinguish inhibitor-positive from inhibitor-negative patients (AUC=0.755, 95% CI: 0.572–0.889, P=0.027). Using a cut-off of >68.7 pg/mL, sensitivity was 62.5%, and specificity was 87.5%, indicating that elevated IL-6 is a specific but moderately sensitive marker for inhibitor status in patients with severe hemophilia A (figure 4).
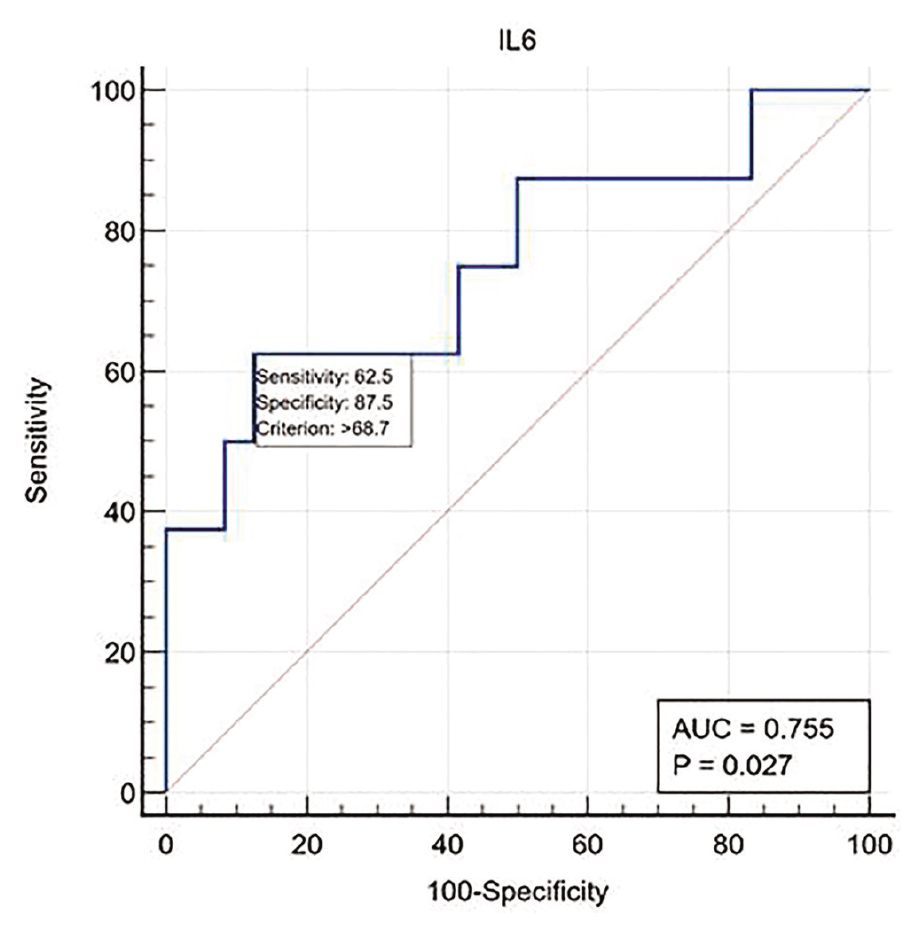
Figure 4.Receiver operating characteristic (ROC) curve analysis of plasma interleukin-6 (IL-6) levels was performed to show whether it can be used as a predictor of inhibitor status in severe HA patients (n=32). The area under the curve (AUC) was 0.755 (95% CI: 0.572–0.889, *P=0.027). The diagonal line represents the reference line of no discriminative ability (AUC=0.5). Using a cut-off of >68.7 pg/mL, sensitivity was 62.5%, and specificity was 87.5%, indicating that elevated IL-6 is a specific but moderately sensitive marker for inhibitor status in patients with severe hemophilia A.
Discussion
In the present study, we evaluated plasma IL-6, a key pro-inflammatory cytokine involved in antibody production, in patients with severe HA to investigate its potential association with inhibitor formation and plasmablast frequencies. Our results demonstrated no significant differences in IL-6 levels between severe HA patients and healthy controls. However, patients with inhibitors exhibited significantly higher IL-6 levels than inhibitor-negative patients and healthy controls. Furthermore, IL-6 levels were shown to be a good predictor of inhibitor development and correlated positively with inhibitor titers, not plasmablast frequencies.
The development of neutralizing antibodies against FVIII, known as inhibitors, remains one of the most significant complications of replacement therapy with FVIII in severe HA patients. The mechanisms underlying why some HA patients develop inhibitors are not fully understood, although studies suggest that specific components of the immune system contribute to this phenomenon.
Previous research supports a role for cytokine patterns in inhibitor development. For instance, Oliveira and colleagues reported that HA patients with inhibitors displayed a more anti-inflammatory and regulatory profile, characterized by elevated IL-4 and IL-10 alongside reduced IFN-γ, IL-2, and IL-5 compared to inhibitor-negative patients and healthy controls.7 However, limited data exist regarding IL-6 role in HA patients. Fan and others observed that elevated IL-6 and granulocyte colony-stimulating factor, along with decreased IL-10, were significantly associated with inhibitor presence.19 Conversely, Pergantou and colleagues found no significant relationship between IL-6 gene polymorphisms and inhibitor development in Greek children with severe HA.20 Knowles and others reported that HA patients had higher IL-6, C-reactive protein, and LPS-binding protein levels than healthy controls, and that elevated IL-6 together with soluble IL-6 receptor α (sIL-6Rα) was associated with bleeding episodes in these patients.15
IL-6 is a multifunctional cytokine produced by a wide range of cells, including monocytes, macrophages, T and B lymphocytes, fibroblasts, endothelial cells, and others. IL-6 mediates its effects via IL-6Rα (CD126) and gp130 (CD130) and influences both local inflammation and systemic physiological processes such as hepatic acute-phase protein synthesis, hematopoiesis, and bone metabolism.9-11 In addition, IL-6 plays a central role in adaptive immunity by promoting B-cell differentiation into antibody-secreting plasma cells and enhancing survival of precursor cells, making it critical in antibody-dependent inflammatory and autoimmune diseases.9-11 In T cells, IL-6 favors Th17 differentiation while suppressing regulatory T cells (Tregs), contributing to chronic inflammation and autoimmunity.21
Excess IL-6 is implicated in diseases such as rheumatoid arthritis, and its blockade with agents such as tocilizumab demonstrates clinical efficacy.9, 10
Based on our findings, elevated IL-6 in severe HA patients may be associated with inhibitor development. Therefore, in addition to immune tolerance induction (ITI); the current standard therapeutic approach to reduce inhibitor levels, targeting IL-6 may represent a promising strategy to limit FVIII-specific plasma cell differentiation and prevent hemophilia-related joint damage. Supporting this notion, Narkbunnam and others demonstrated that hemophilic mice treated with anti-IL-6R alongside FVIII replacement therapy showed improved survival and reduced acute joint pathology.22
We acknowledge the lower mean age in inhibitor-positive versus inhibitor-negative patients. This finding aligns with the established natural history of inhibitor development, which typically occurs during early childhood within the first 50–100 exposure days to FVIII replacement therapy. Similar age patterns have been consistently reported in the literature.23, 24 Importantly, multivariate analysis confirmed that the association between inhibitor status and IL‑6 levels remained significant after adjusting for age, treatment type, and FVIII type, indicating that baseline age and treatment type did not independently predict the outcome or substantially confound our finding. However, FVIII type itself was also a significant factor. Given that this is an exploratory finding, cautious interpretation is warranted, and validation in future studies is necessary. Another limitation of our study is the small number of inhibitor-positive patients. The small sample size of the inhibitor-positive group reflects the inherent rarity of the condition in our region, not selective inclusion or inadequate recruitment. As the sole hemophilia referral center in Fars province, we included all eligible patients, achieving complete capture of the available population. No additional inhibitor-positive patients were available, minimizing selection bias. However, post hoc power analysis using a general linear model (95% confidence intervals, α=0.05) demonstrated observed power values of 0.898 for the primary comparisons, exceeding the conventional 0.80 threshold. Thus, despite the modest absolute sample size, the study was adequately powered to detect the observed effects. Nevertheless, larger multicenter studies are needed to validate our findings. Additionally, monitoring dynamic changes in IL-6 levels during ITI therapy could provide further insights into its role in regulating inhibitor formation. Furthermore, evaluating other pro- and anti-inflammatory cytokines, including IL-4, IL-21, and IL-10, as well as factors influencing B-cell survival and plasma cell maintenance, such as B-cell Activating Factor (BAFF) and A Proliferation-Inducing Ligand (APRIL), may offer valuable information on the contribution of the immune system to the pathophysiology of HA.
Conclusion
In conclusion, plasma IL-6 levels are significantly associated with inhibitor development in severe HA patients and demonstrate fair to good discriminative ability for identifying inhibitor status. Therefore, IL-6 may serve as a potential biomarker for inhibitor risk assessment, although larger prospective studies are needed to confirm these preliminary findings and explore its therapeutic potential.
Acknowledgment
This study was conducted as part of the MD thesis of Helmi Helmi at Shiraz University of Medical Sciences (grant number 28651).
Authors’ Contribution
T.Z: Data extraction, analysis, drafting, and reviewing the manuscript; OR.Z, A.T, A.SH, H.H, H.G, and SH.P: Data extraction, performing the research, and reviewing the manuscript; N.A: Study design, conceptualization, data extraction, interpretation and analysis, performing the research, drafting and reviewing the manuscript. All authors have read and approved the final manuscript. They agree to be accountable for all aspects of the work, ensuring that questions related to the accuracy or integrity of any part of the work are appropriately investigated and resolved.
Declaration of AI
The authors declare that no artificial intelligence tools were used in the preparation, analysis, or writing of this manuscript.
Conflict of Interest
None declared.
References
- Gouw SC, van den Berg HM, le Cessie S, van der Bom JG. Treatment characteristics and the risk of inhibitor development: a multicenter cohort study among previously untreated patients with severe hemophilia A. J Thromb Haemost. 2007; 5:1383-90. DOI | PubMed
- Seaman CD, Xavier F, Ragni MV. Hemophilia A (Factor VIII Deficiency). Hematol Oncol Clin North Am. 2021; 35:1117-29. DOI | PubMed
- Spena S, Garagiola I, Cannavo A, Mortarino M, Mannucci PM, Rosendaal FR. Prediction of factor VIII inhibitor development in the SIPPET cohort by mutational analysis and factor VIII antigen measurement. J Thromb Haemost. 2018; 16:778-90. DOI | PubMed
- Merlin S, Follenzi A. Escape or Fight: Inhibitors in Hemophilia A. Front Immunol. 2020; 11:476. Publisher Full Text | DOI | PubMed [ PMC Free Article ]
- Astermark J. Why do inhibitors develop? Principles of and factors influencing the risk for inhibitor development in haemophilia. Haemophilia. 2006; 12:52-60. DOI | PubMed
- Oldenburg J, Pavlova A. Genetic risk factors for inhibitors to factors VIII and IX. Haemophilia. 2006; 12:15-22. DOI | PubMed
- Oliveira CA, Velloso-Rodrigues C, Machado FC, Carvalho BN, Gentz SH, Martins-Filho OA. Cytokine profile and FVIII inhibitors development in haemophilia A. Haemophilia. 2013; 19:e139-42. DOI | PubMed
- Wight J, Paisley S. The epidemiology of inhibitors in haemophilia A: a systematic review. Haemophilia. 2003; 9:418-35. DOI | PubMed
- Mihara M, Hashizume M, Yoshida H, Suzuki M, Shiina M. IL-6/IL-6 receptor system and its role in physiological and pathological conditions. Clin Sci (Lond). 2012; 122:143-59. DOI | PubMed
- Tanaka T, Narazaki M, Kishimoto T. IL-6 in inflammation, immunity, and disease. Cold Spring Harb Perspect Biol. 2014; 6:a016295. Publisher Full Text | DOI | PubMed [ PMC Free Article ]
- Narazaki M, Kishimoto T. The Two-Faced Cytokine IL-6 in Host Defense and Diseases. Int J Mol Sci. 2018; 19Publisher Full Text | DOI | PubMed [ PMC Free Article ]
- Zhang C, Zhang X, Chen XH. Inhibition of the interleukin-6 signaling pathway: a strategy to induce immune tolerance. Clin Rev Allergy Immunol. 2014; 47:163-73. DOI | PubMed
- Muraguchi A, Hirano T, Tang B, Matsuda T, Horii Y, Nakajima K. The essential role of B cell stimulatory factor 2 (BSF-2/IL-6) for the terminal differentiation of B cells. J Exp Med. 1988; 167:332-44. Publisher Full Text | DOI | PubMed [ PMC Free Article ]
- Wu Y, El Shikh ME, El Sayed RM, Best AM, Szakal AK, Tew JG. IL-6 produced by immune complex-activated follicular dendritic cells promotes germinal center reactions, IgG responses and somatic hypermutation. Int Immunol. 2009; 21:745-56. Publisher Full Text | DOI | PubMed [ PMC Free Article ]
- Knowles LM, Wolter C, Menger MD, Laschke MW, Beyer L, Grun U. Activation of the Acute-Phase Response in Hemophilia. Thromb Haemost. 2023; 123:867-79. Publisher Full Text | DOI | PubMed [ PMC Free Article ]
- Wojdasiewicz P, Poniatowski LA, Nauman P, Mandat T, Paradowska-Gorycka A, Romanowska-Prochnicka K. Cytokines in the pathogenesis of hemophilic arthropathy. Cytokine Growth Factor Rev. 2018; 39:71-91. DOI | PubMed
- Zekavat OR, Movahednezhad Y, Shahsavani A, Haghpanah S, Shokrgozar N, Golmoghaddam H. Abnormal frequency of the memory B cell subsets and plasmablasts in patients with congenital severe hemophilia A: correlation with “Inhibitor” formation. Blood Res. 2024; 59:16. Publisher Full Text | DOI | PubMed [ PMC Free Article ]
- Irigoyen MB, Felippo ME, Primiani L, Candela M, Bianco RP, De Bracco MM. Severe haemophilia A patients have reduced numbers of peripheral memory B cells. Haemophilia. 2012; 18:437-43. DOI | PubMed
- Fan MN, Shen T, Konkle BA, Cai X, Chao TY, Manco-Johnson M. Exploration of biomarkers for inhibitor development in persons with hemophilia A. Res Pract Thromb Haemost. 2025; 9:102877. Publisher Full Text | DOI | PubMed [ PMC Free Article ]
- Pergantou H, Varela I, Moraloglou O, Economou M, Spanou K, Kapsimali Z. Impact of HLA alleles and cytokine polymorphisms on inhibitors development in children with severe haemophilia A. Haemophilia. 2013; 19:706-10. DOI | PubMed
- Korn T, Bettelli E, Oukka M, Kuchroo VK. IL-17 and Th17 Cells. Annu Rev Immunol. 2009; 27:485-517. DOI | PubMed
- Narkbunnam N, Sun J, Hu G, Lin FC, Bateman TA, Mihara M. IL-6 receptor antagonist as adjunctive therapy with clotting factor replacement to protect against bleeding-induced arthropathy in hemophilia. J Thromb Haemost. 2013; 11:881-93. Publisher Full Text | DOI | PubMed [ PMC Free Article ]
- Borhany M, Kumari M, Shamsi T, Naz A, Farzana T. Frequency of factor VIII (FVIII) inhibitor in haemophilia A. J Coll Physicians Surg Pak. 2012; 22:289-93. PubMed
- Arshad S, Singh A, Awasthi NP, Kumari S, Husain N. Clinicopathological parameters influencing inhibitor development in patients with hemophilia A receiving on-demand therapy. Ther Adv Hematol. 2018; 9:213-26. Publisher Full Text | DOI | PubMed [ PMC Free Article ]


